clinicians.dev

clinicians.dev

A community of clinical experts super-powered with skills in agentic engineering. Our roots are in coding and clinical medicine. We know how to create and supervise LLMs writing Python, SQL, R, JS, HTML. We love startups, regs, policy, UI/UX, data viz, project management, informatics. We want to create the medicine of the next 100 years.

today · the wire

The Wire

What you'll be asked today — and what to say back. A couple that caught my eye this morning; the rest are on the wire.

CMS wants to stop paying the people who actually run your remote monitoring program.

Becker's Hospital Review · Sept 19, 2026

A colleague in finance asked me whether the letters going out about a Medicare remote-monitoring rule put our RPM revenue at risk on January 1. Short answer: if your monitoring staff sit inside a vendor rather than on your own payroll, yes. The 2027 Physician Fee Schedule proposal would pay for remote physiologic and remote therapeutic monitoring only when the clinical staff furnishing the service are employed by the billing practice — not contracted from a third party. They don't have to be on-site, but the employment relationship has to be yours. More than 230 organizations, including 35 health systems, have now signed on asking CMS to drop it. The exposure isn't evenly spread — large service lines can absorb hiring, and the places that break are the small and rural practices RPM has been extending into precisely because they can't staff it themselves. The number worth pulling before your next finance meeting isn't total RPM revenue. It's RPM revenue by staffing model, and what it would cost to bring the contracted piece in-house if the rule lands as written.

HatersCMS's stated concern is that outsourcing fragments care and leaves the billing clinician insufficiently involved. Which is true, and also a description of roughly every arrangement Medicare currently pays for without comment. The rule doesn't end absentee supervision; it just requires the absentee to be on your W-2.

When an AI agent calls our front desk to book a patient, who is it acting for?

Fierce Healthcare · Sept 16, 2026

The patient — or whoever is paying for the agent. Ferry Health came out of stealth with $9M in seed funding from a16z and Index to run voice and digital agents that call provider offices directly, verify network status, and book the appointment on the patient's behalf. Everyone's been building the agent that answers the phone; Ferry is building the one that places the call, and that flips the problem your access team has been solving for two years. A scheduling bot on your side of the line can be governed — you set its hours, its rules, its escalation path. One on the patient's side arrives as an ordinary call to an ordinary human who has no way to tell it apart from a person, no script for it, and no policy about what to disclose. That's the question worth asking this week: not whether to buy one, but what your schedulers do when they realize they're talking to software. Worth noting who the customers are, too — health systems, payers, and care navigation platforms. The agent calling you may be working for your own contracted navigator.

Your ambient vendor stopped writing notes and started reading the whole chart.

229 Project · Bill Russell with Sarah Richardson · Sept 21, 2026

The number to carry into your next vendor call is 9,000% — the increase in EHR request volume that systems furthest along with ambient AI are reporting. The cause is scope creep in the product, not in your usage: the tool that used to generate a note now pulls the longitudinal record, checks revenue cycle, and queries other services, on a machine-to-machine cadence instead of a human one. A person checks when they need to know; an agent checks every five minutes because polling is free to the thing doing the polling. It starts to feel like an internal denial-of-service inside your own EHR, and it's the cost nobody put in the ambient business case. The concrete ask: get read-volume and API-call metrics per AI vendor, per month, and put a ceiling in the next contract.

80/20Everything else in the AI governance binder can wait. The one artifact that changes your risk this quarter is a per-vendor log of EHR API calls with a rate ceiling written into the contract. Without it, you find out about the traffic when the EHR slows down at 10 a.m. on a Tuesday, and the vendor's answer is that usage grew.

The clinical agent worth copying is the one that refuses to answer.

Nature Medicine · Sept 2026

TU Dresden researchers built an on-premises, LLM-powered clinical agent designed around what they call selective autonomy — it reports high diagnostic accuracy on standardized benchmarks and routes its uncertain outputs to a clinician instead of answering. Two things here matter more than the accuracy number. First, on-premises: the architecture assumes the model runs inside the institution, which sidesteps most of the data-path objection that stalls clinical AI procurement and turns the compute cost into a capital conversation instead of a privacy one. Second, abstention is treated as a designed behavior rather than a failure. Almost every clinical AI product on the market answers every time it's asked, because a confidence threshold that produces silence is hard to demo and harder to price. But abstention is what makes a tool safe to put in front of a resident, and a vendor who can tell you their abstention rate — and what happens to those cases — is telling you something a benchmark score can't.

Has OpenEvidence already peaked?

Health Tech Nerds · Sept 20, 2026

The read circulating among health tech investors this week is that OpenEvidence's latest round is a quiet down-note rather than a milestone — a raise around $15B, after reports earlier this year that it was weighing $200M at a $20B valuation. Take the exact numbers as reported rather than confirmed, but the direction is the signal worth having. If the most-adopted clinical reference tool on the market is repricing, the thing being repriced isn't usage — physician adoption hasn't fallen — it's the belief that free point-of-care answers convert into a durable business. That's the question worth having ready when someone asks why a company clinicians love is worth less than it was in the spring.

clinical AI product decisions

Clinical AI Labs

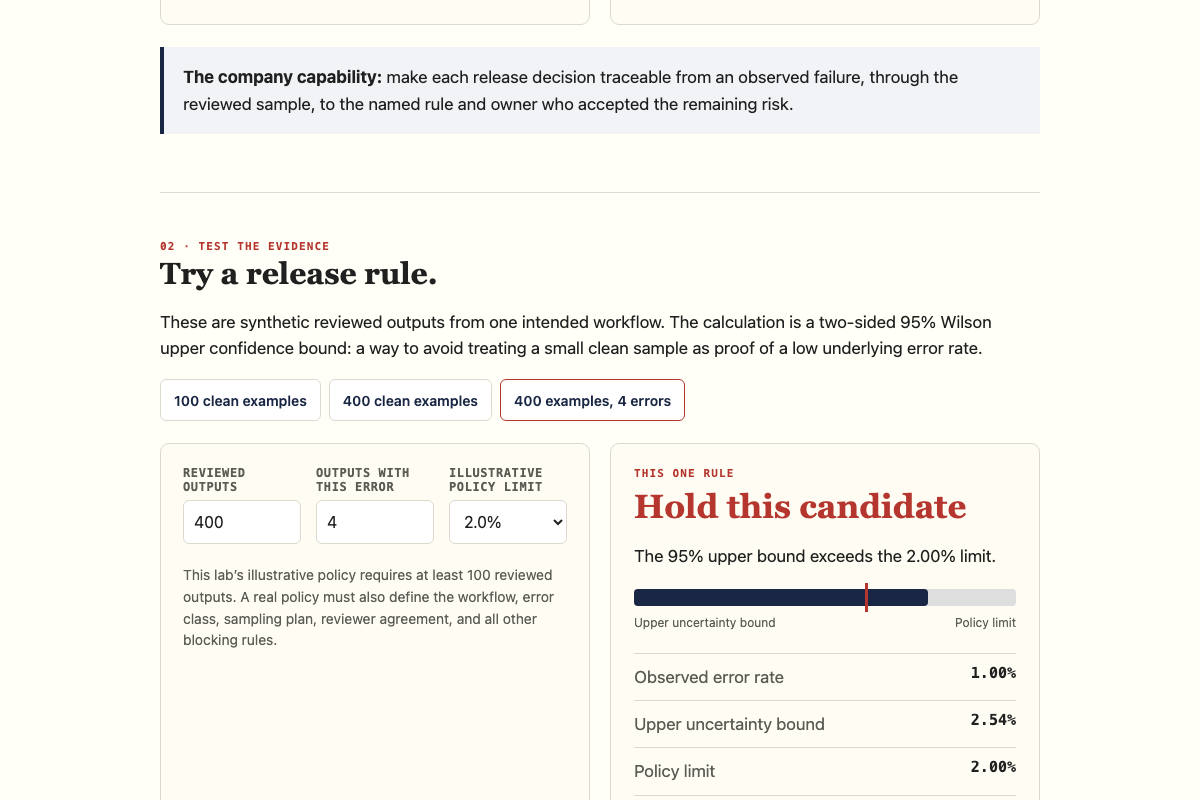
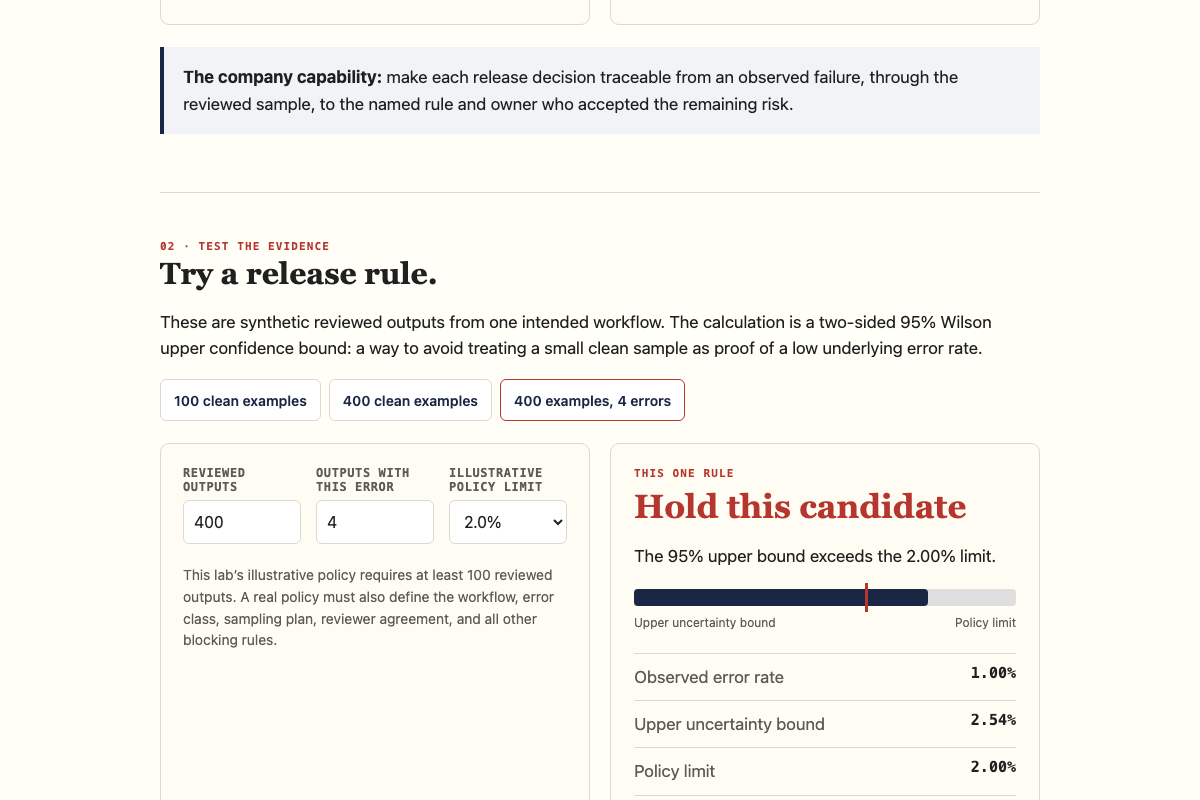
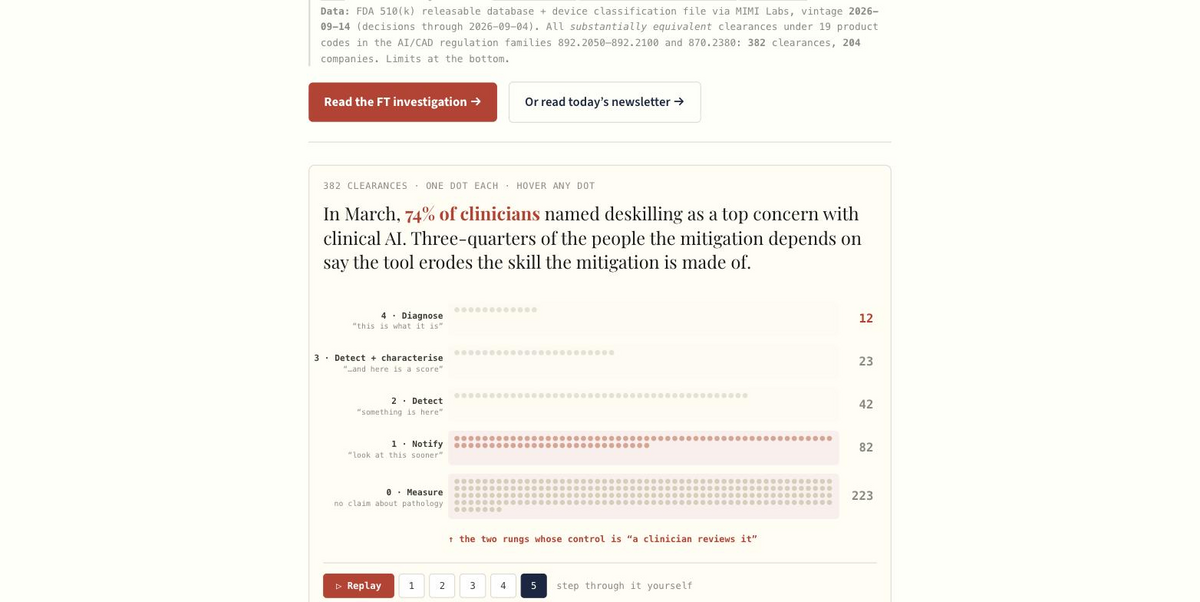
Work through the decisions behind a clinical AI product: what to measure, what to trust, and when to release.

Browse all AI Labs →

learn by doing

Interactives

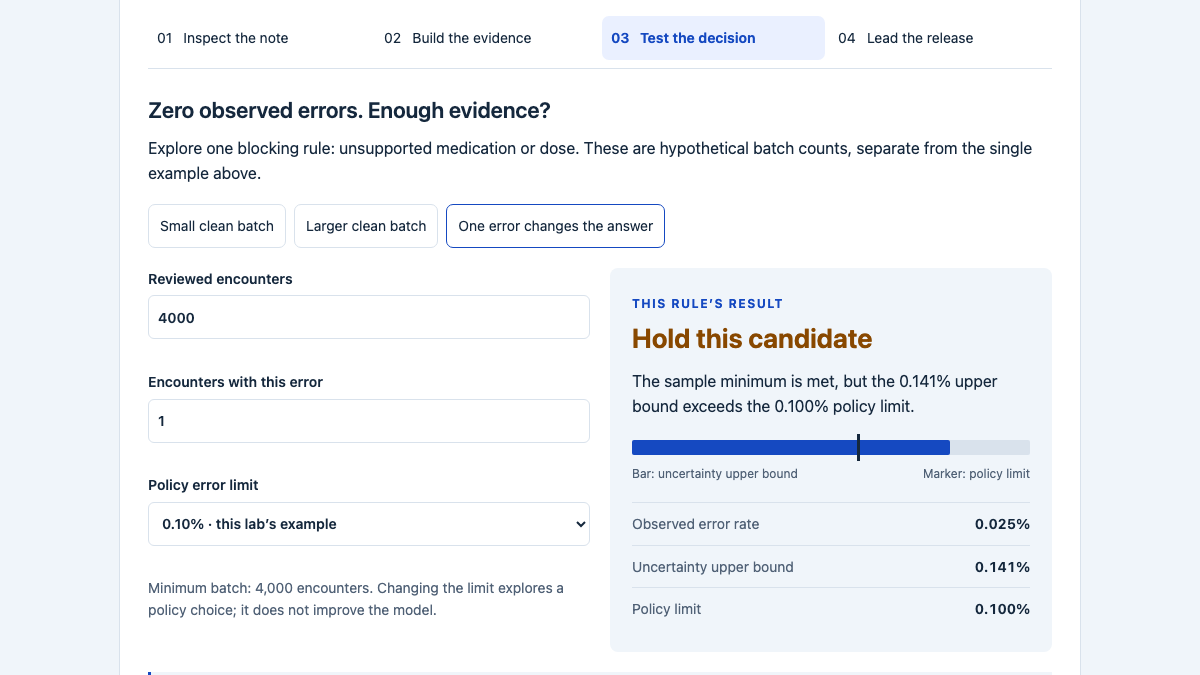
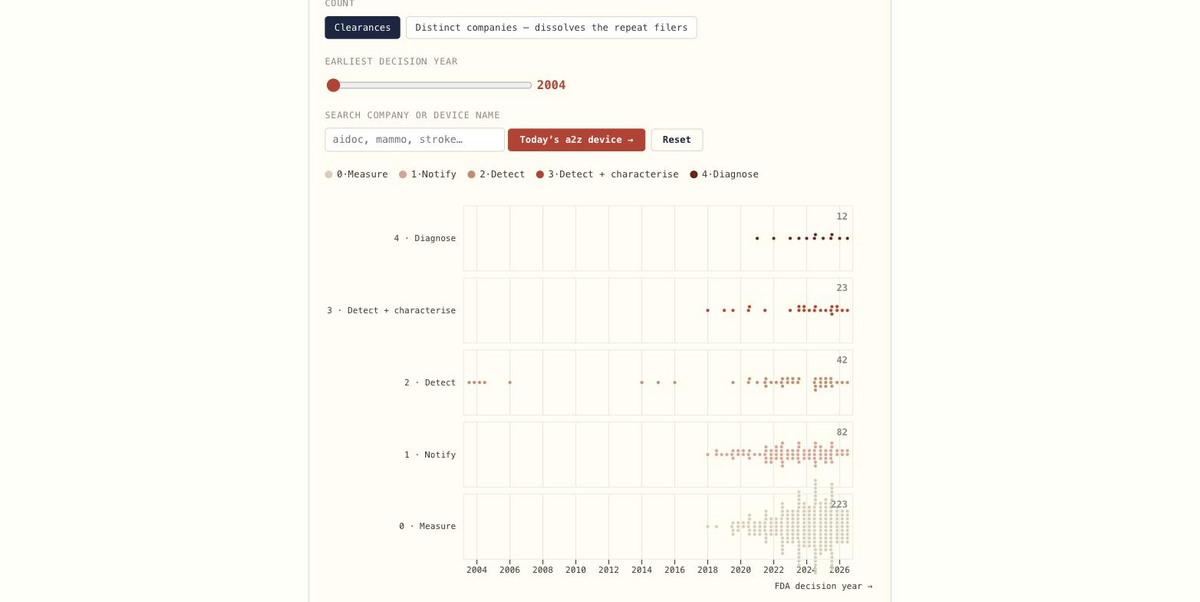
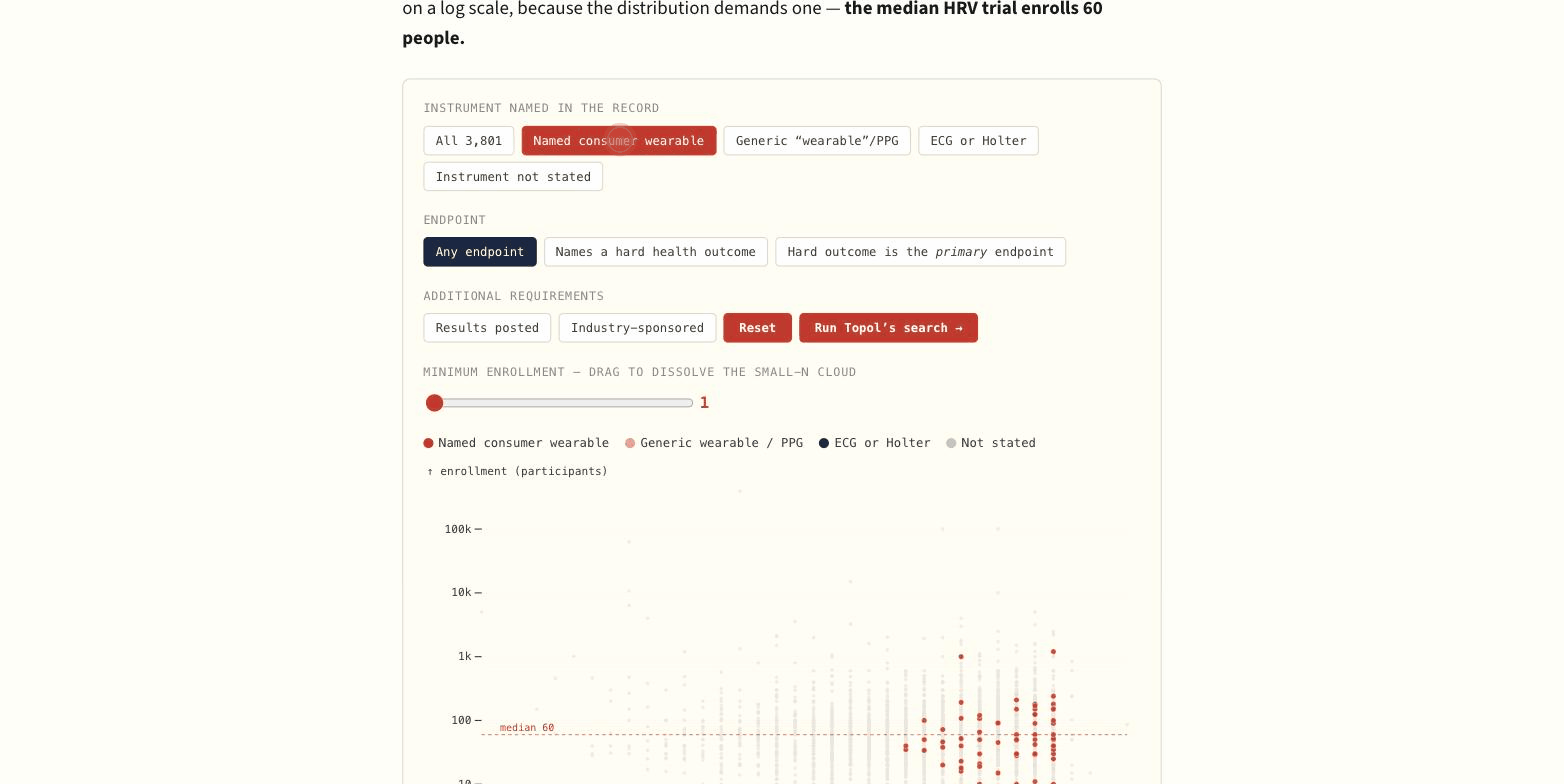
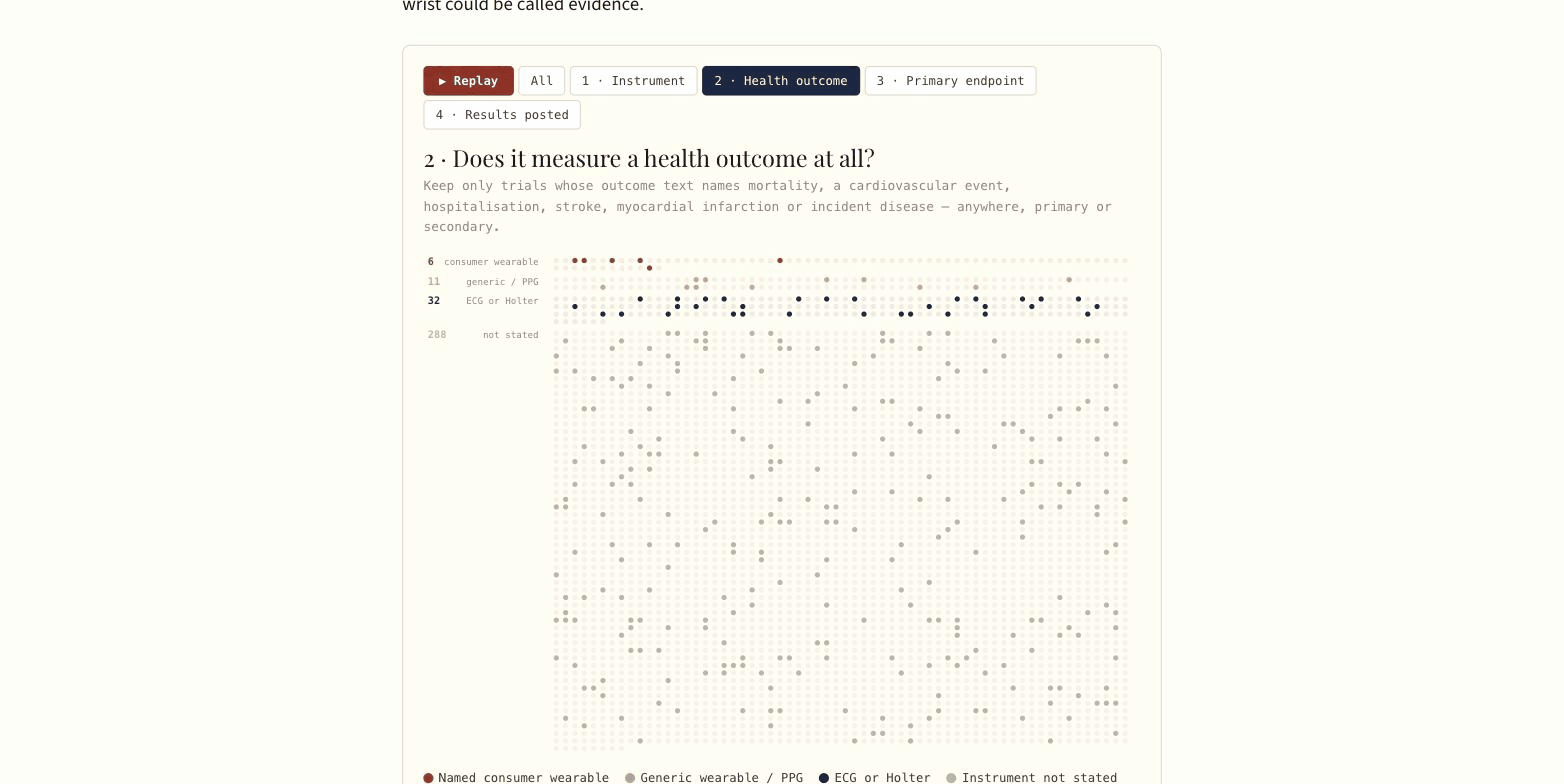
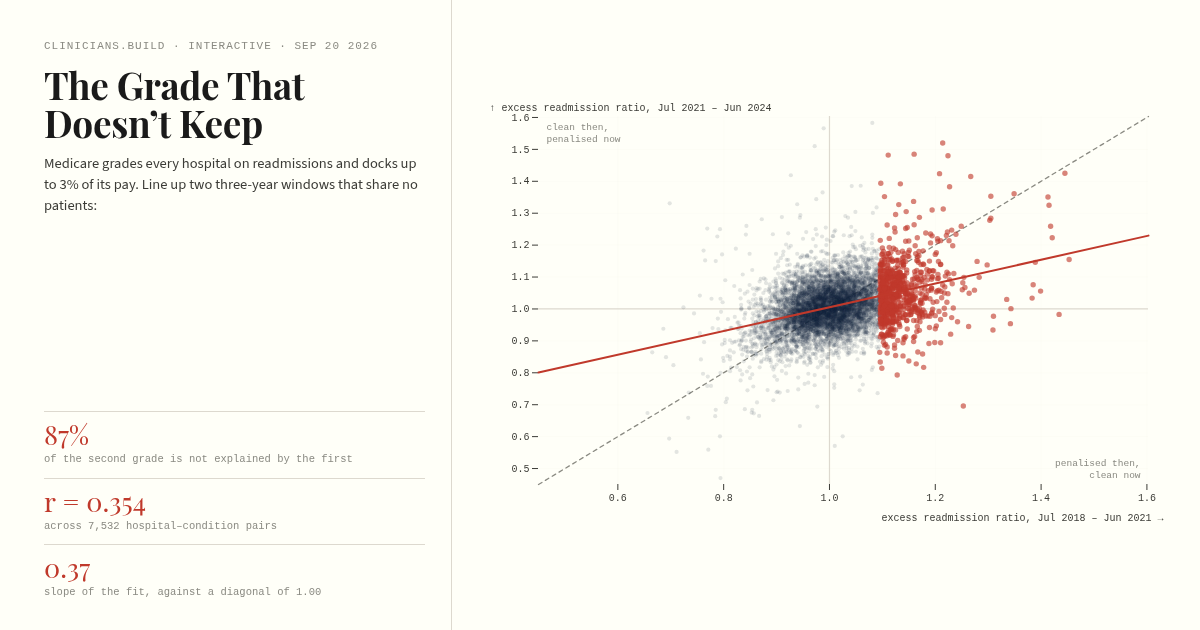
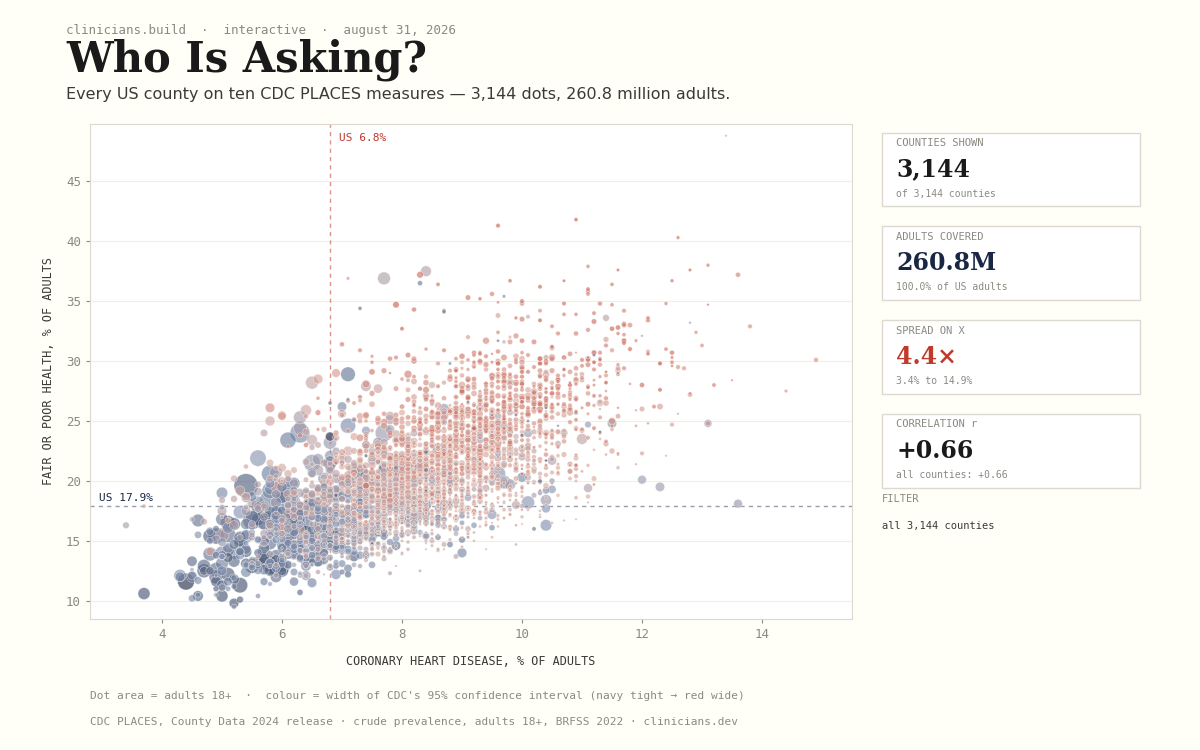
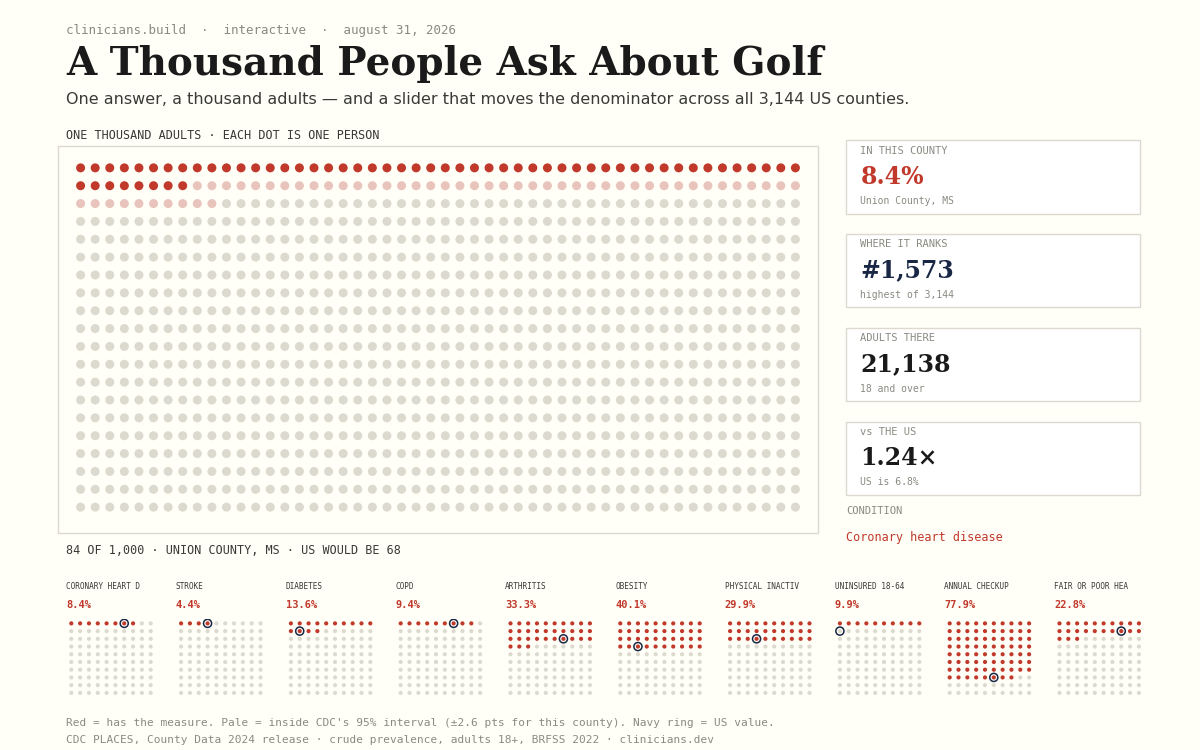
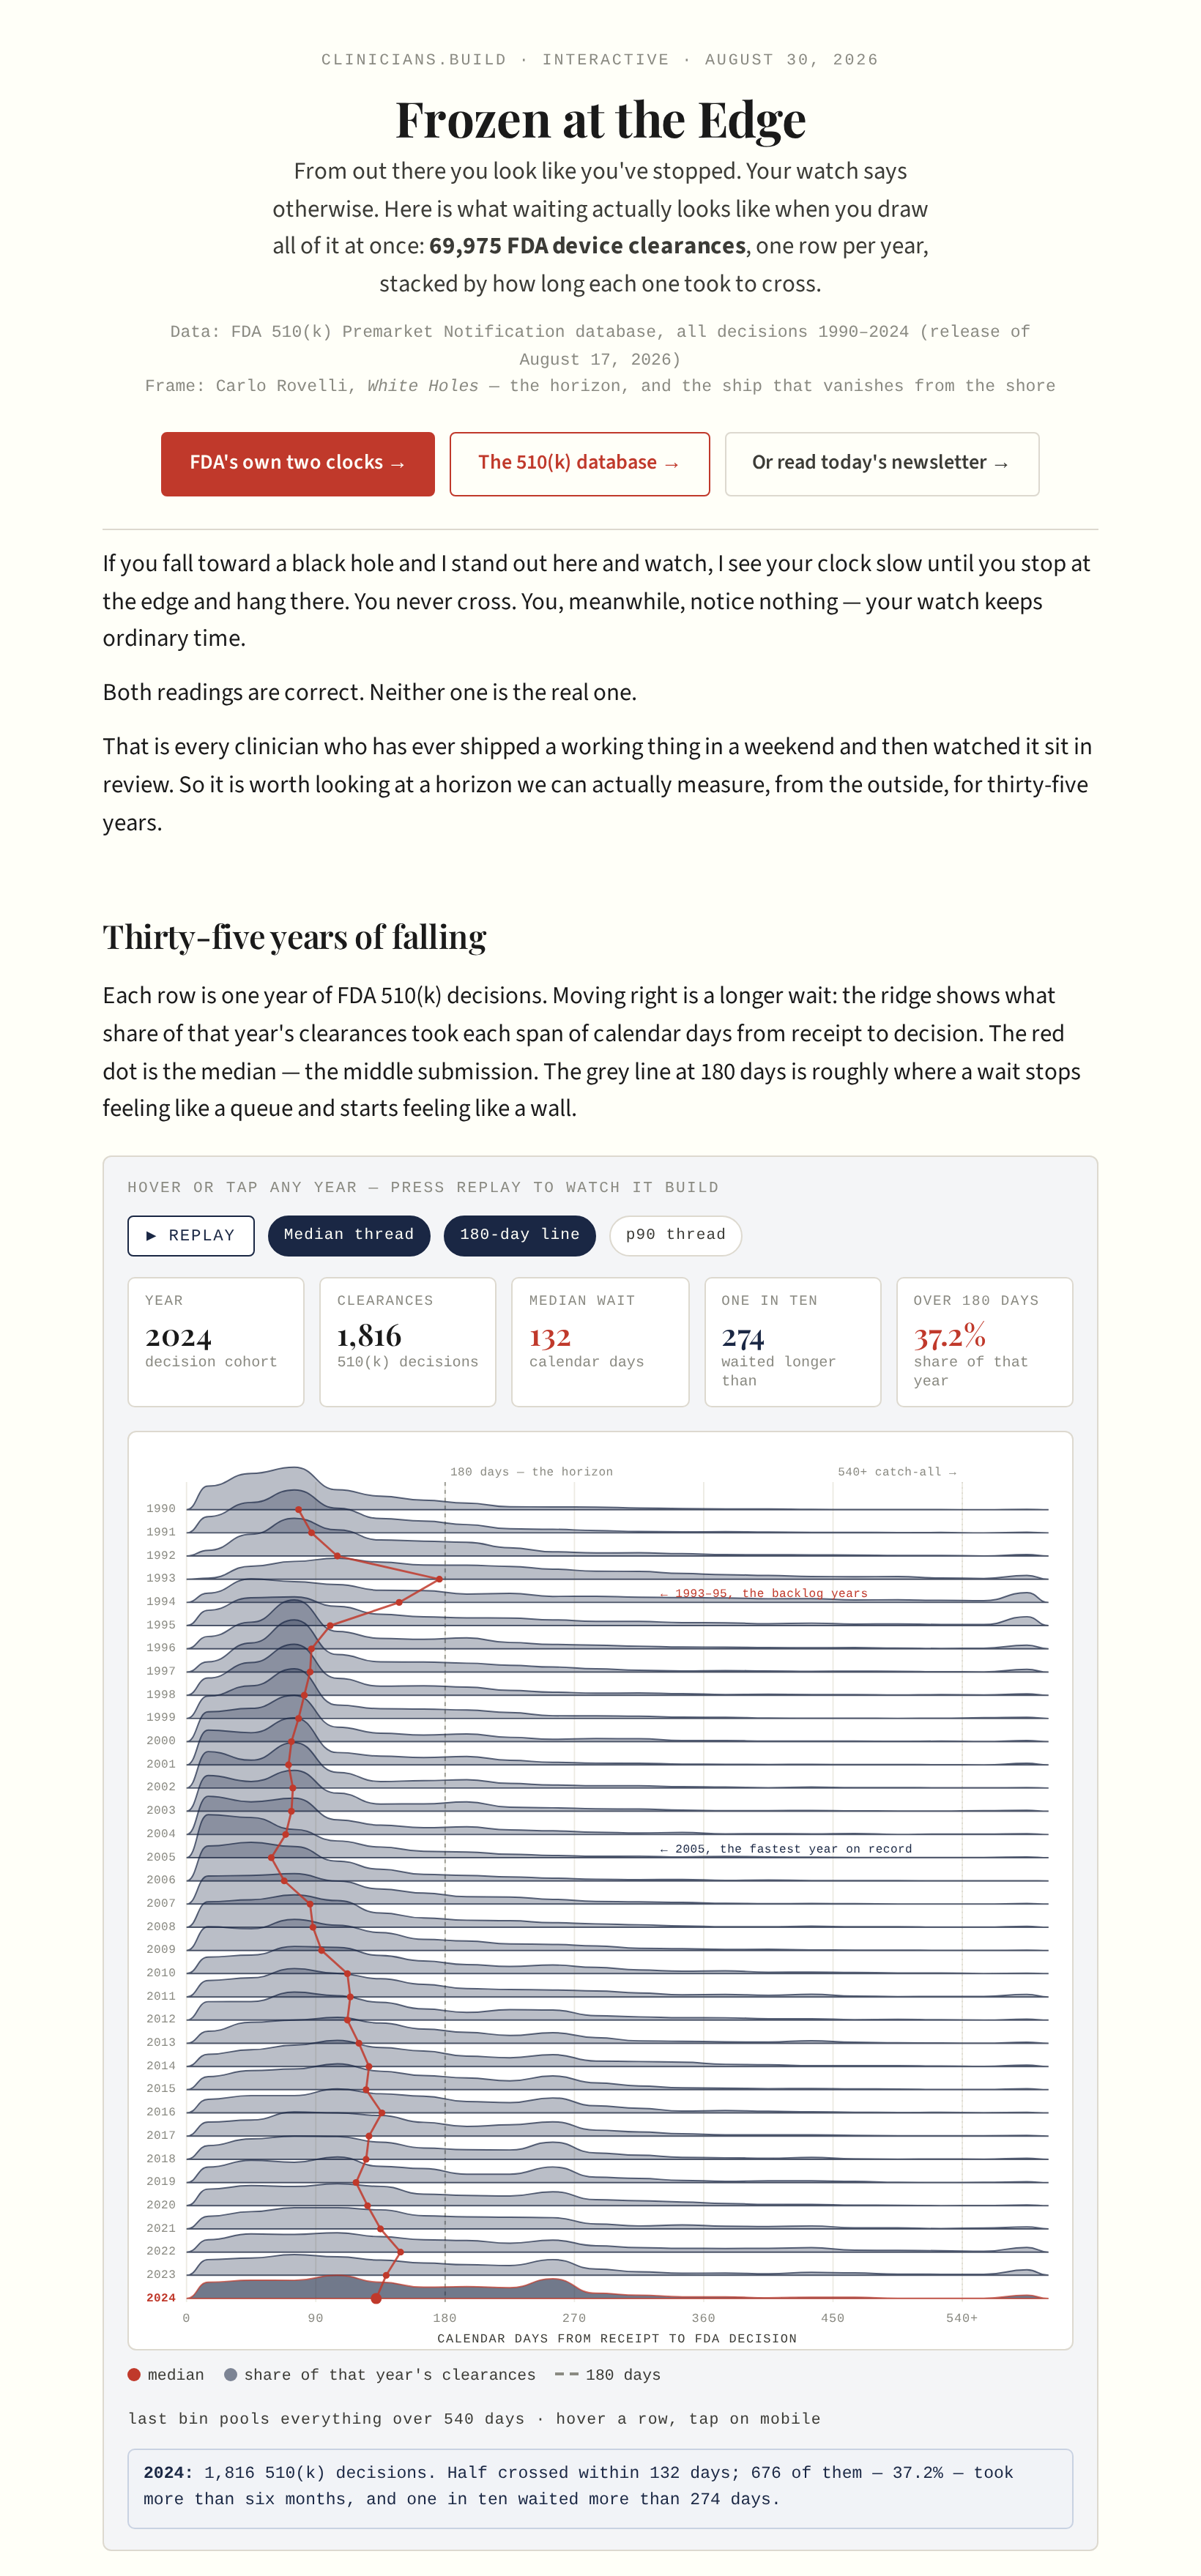
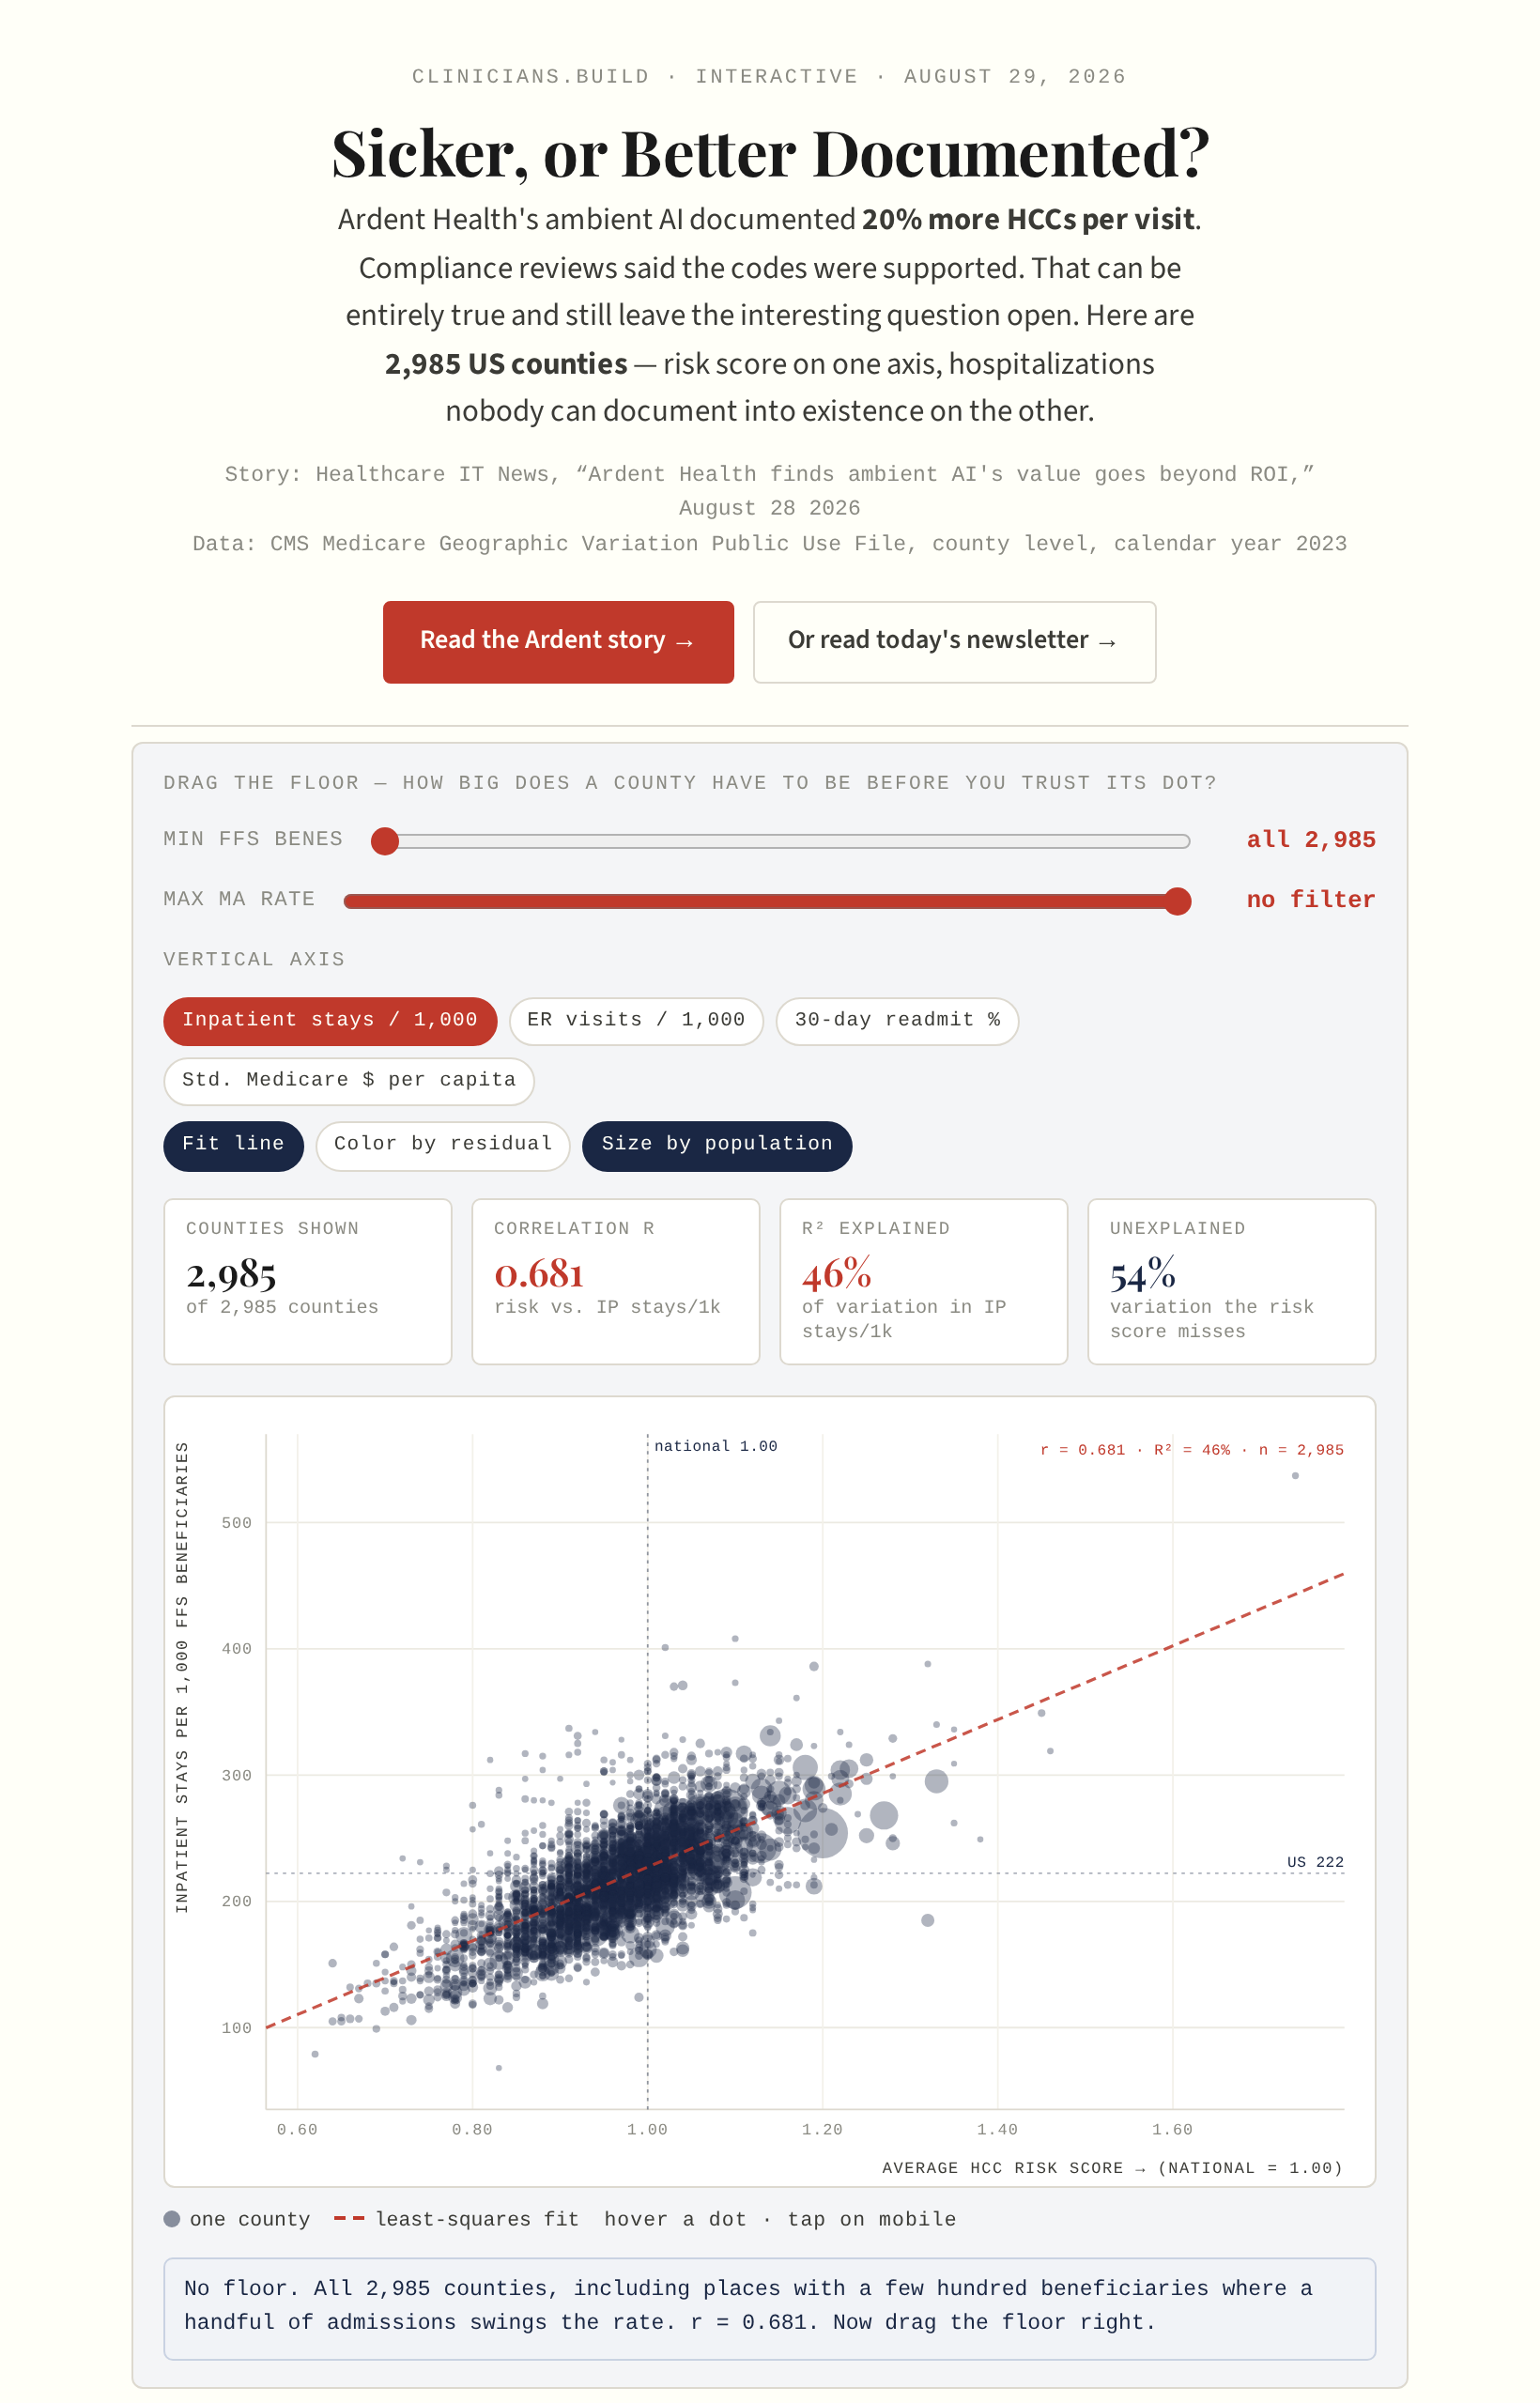
Companion experiences for the newsletter — don't just read about it, try it.

from the substack

Builder's Briefing

The newsletter — what shipped this week, what it means, and what to build next. A couple of recent issues.

01 · Learn

AI & agentic engineering

The foundational reads, the tools clinicians-who-code are actually using, and the loop that ships.

Context engineering — the foundation

Effective Context Engineering for AI Agents

Anthropic's foundational guide.

Building Effective Agents

When to use workflows vs. agents, and how to structure both.

2026 Agentic Coding Trends Report

How teams are actually shipping with agents.

Learn CLAUDE.md / AGENTS.md

The spec files that make agentic coding repeatable.
🔁 The Ralph Wiggum Pattern — the loop that ships. Tight spec → agent implements → you verify → adjust spec → repeat. Just keep going.

Tools of the trade

ToolBest forNotes
Claude CodeComplex multi-file work, architectureTerminal-native, large context. The power tool. Good for non-code tasks too.
CursorDaily coding with autocomplete + inline editsAI IDE, huge user base.
WindsurfBudget entry, Cascade collaborationAI-native editor.
Copilot / Codex CLIRepo-native GitHub workflowsTight GitHub integration.

Skills marketplaces

Claude Code Marketplace

Curated agent skills collection.

Claude Skills (232+)

Cross-agent skills for Claude Code, Codex, Gemini CLI, Cursor.

Awesome Claude Plugins

Plugin adoption metrics.

claudemarketplaces.com

4,200+ skills, 770+ MCP servers.

Healthcare MCPs

AWS HealthLake MCP

Amazon's healthcare data MCP server.

Agent Care

EMR integration with FHIR for agentic AI.

Keragon

300+ native healthcare integrations, FHIR protocol support.

Superpowers Framework

Agentic skills framework for coding agents.

Agentic frameworks & orchestration

02 · Communities

Communities, courses, substacks

Where clinician innovators and clinician builders are hanging out.

HealthTechNerds

Active Slack, all different backgrounds.

Tuva

Active Slack community.

CodeRx

Pharma, healthcare, technology.

Mimilabs

Medicare data (paid).

DiMe

Research, clinical, digital medicine.

Design for Healthcare

UX, UI, healthcare products.

HealthTech Hang

Networking + resources.

Physician Innovator

Entrepreneurship, medical innovation.

SoPE

Healthcare, entrepreneurship, VC (paid).
03 · Build stack

EHRs, FHIR, fake patients

The pipes you'll need when you're actually building.

EHRs & FHIR

🔑 SMART-on-FHIR / OAuth flowfhir.epic.com/Documentation?docId=oauth2

Generate fake patients

MakeData

Synthetic healthcare datasets — FHIR, JSON, CSV. Privacy-safe, immediate.

Patient Creator GPT

ChatGPT custom GPT for fake cases.

Synthea

MITRE's synthetic patient generator — the classic.

FHIR Personas

Synthea patients curated for interesting characteristics.
04 · Datasets

Clinical datasets worth knowing

From CXRs to genomes to ICU waveforms. Filter by name, modality, or license.

NameRelevanceLicense
ReXGradient-160K160k multi-site CXR + reports — vision-language radiology sandbox.Harvard DUA, non-commercial
CheXpert PlusLarge paired CXR–report set; benchmarked in many papers.Stanford DUA, free research
Endoscapes 2023Open laparoscopic chole frames — segmentation / CVS detection.CC BY-NC-SA 4.0
Surg-3M3M surgical frames powering "SurgFM" foundation model.TBA, expect research-only
AFRICAI RepositoryImaging sets from African centres — fairness & domain shift.Mixed open licenses
OpenOximetryWaveforms + skin-tone data for pulse-ox bias work.PhysioNet credentialed
DeepLesion32k CT slices with bounding-box lesions; detection / tracking.NIH DUA, research-only
BioASQ Synergy 2024Biomedical Q-A pairs — LLM eval set.CC BY 2.5
CliniFactClinical-trial fact-checking corpus — fine-tune retrieval / RAG.MIT
Hallucination AnnotationsDoctor- & LLM-written discharge summaries with token-level labels.PhysioNet credentialed
Clinical-Trial Eligibility QAQA pairs linking MIMIC-IV to apixaban RCT criteria.PhysioNet credentialed
PIFIRWearable PPG/ECG for arrhythmia-free interval prediction.PhysioNet restricted
GREGoR R02Rare-disease genomic + phenotypic harmonised data.dbGaP controlled
Synthetic Rare-Disease EHRsBenchmark synthetic EHRs for low-prevalence conditions.CC BY
Korea4K4k Korean genomes — ancestry diversity for variant calling.EGA controlled
OpenNeuro20k+ public neuro-imaging sessions; BIDS-ready.CC0 / CC BY-SA
Bridge2AI-VoiceMultimodal speech (voice, vitals) for health AI.PhysioNet restricted
PMDB Pain MonitoringWearable IMU + self-report pain diary.CC BY 4.0
DREAMT Wearable SleepApple Watch PSG pairs for sleep-staging models.PhysioNet restricted
MC-MEDMulti-condition medical dialogue (GPT / human).PhysioNet credentialed
Wearable Stress DatasetSmartwatch vitals + stress labels — mental health ML.PhysioNet restricted
MIMIC-IV v3.1Flagship 380k-patient de-id EHR; ED + ICU tables.PhysioNet credentialed + CITI
MIETICItalian clinical-notes corpus with entity spans.PhysioNet credentialed
ODD (Opioid Behavior)Annotated notes for opioid-related behaviour NLP.PhysioNet credentialed
UK Biobank500k UK adult cohort — EHR, surveys, genetics.Controlled access
All of Us (NIH)1M-goal US cohort — EHR, surveys, genomics, wearables.Registered + Controlled tiers
TCGA~11k patients across 33 cancer types — multi-omics + clinical.Partially open
AmsterdamUMCdbFirst open European ICU DB — 23k admissions.DUA required
ADNILongitudinal Alzheimer's — serial MRI/PET, clinical, biomarkers.Free non-commercial
ABCD Study10k youths — neuroimaging, cognitive, mental health, genetic.NIMH controlled access
NHANES (CDC)US national survey — health, nutrition, lab data.Public domain
CheXpert (original)224k chest X-rays, 65k patients — labeled findings.Free non-commercial
EchoNet-Dynamic10k+ cardiac ultrasound videos with EF + ventricle volumes.Non-commercial
SyntheaRealistic synthetic patient records — full EHR.MIT
1000 GenomesWGS from ~2,500 diverse individuals — human variation reference.Open access
DementiaBank (Pitt)Speech recordings + transcripts from Alzheimer's patients + controls.Consortium access
VitalDB6,300+ surgeries with continuous high-freq vital sign waveforms.Open, registration + DUA
Medical Segmentation Decathlon10 open datasets for 3D medical image segmentation.CC BY-SA 4.0
PANDA10k+ prostate biopsy WSIs with Gleason grades.CC BY 4.0
05 · Conferences

AI & health conferences

Borrowed from Raihan Faroqui's healthcare AI resource guide. Filter to find your tribe.

06 · Jobs

Job boards that don't suck (as much)

What they are. Not endorsements — just the lay of the land.

07 · Startup

So you want to build a startup

But don't know anything about tech/stack, marketing/sales, finances, management.

08 · Life

Life hacking / survival

Because clinician-builders need to not burn out.

09 · Experiments

LLM matrix tests (alpha)

Testing out LLMs with fake patient scenarios generated by GPTs.

10 · Archive

Past events

Where we've been.

Fall 2025 Conference
TimeSpeakerTalk
1:00pTBDWelcome
1:10–1:22pJosh Mandel, MDConversational Interoperability for Prior Auth and Beyond — MCP, A2A, and the Unreasonable Effectiveness of Making Data Accessible
1:35–1:47pJung Hoon Son, MDData CPR: How LLMs Revive Buried Clinical Insights
2:00–2:12pJason Theobald, MDContain Multitudes: A Docker Intro
2:25–2:37pCalvin Johnston, MDSoftware Design and Family Medicine: Overlapping skill sets
2:50pTBDWrap-up
Summer 2025 Conference
TimeSpeakerTalk
1:00pKevin Maloy, MDWelcome
1:10–1:22pVishnu Ravi, MDDigital Health that Ships: An Open Framework You Can Use Today
1:35–1:47pAlex Dummet, MDTopic TBD
2:00–2:12pPawan Jindal, MDStartup Survival 101: A Clinician's Guide
2:25–2:37pOmar Usman, MDChange Data Capture (CDC): A Defiant Approach
2:50pKevin Maloy, MDWrap-up
Fall 2024 Conference (Nov 9, 2024)
TimeSpeakerTalk
1:00pKevin Maloy, MDWelcome
1:10–1:22pPaulius Mui, MDFrom 0 to 1: Becoming a Clinician Who Codes
1:30–1:42pBrian Fung, PharmDPath of the Clinician Engineer
1:50–2:02pJoe Izzo, MDThe Coding CMIO — it's okay to get your hands dirty
2:10–2:22pKarambir Khangoora, MDLearning to Code as a Clinician: Building Medagogy
2:30–2:42pJoey LeGrand, PharmDOne Brain Can Be Better Than Two
2:50pKevin Maloy, MDWrap-up
Podchat — Should Hospitals Mandate GenAI Training? (Aug 29, 2024)

Listen to a short podcast, then talk about whether it's right or wrong. Original from Bill Russell at This Week Health. → Meetup event